
EBOO Therapy During Cancer Treatment: The Timing Question Comes First
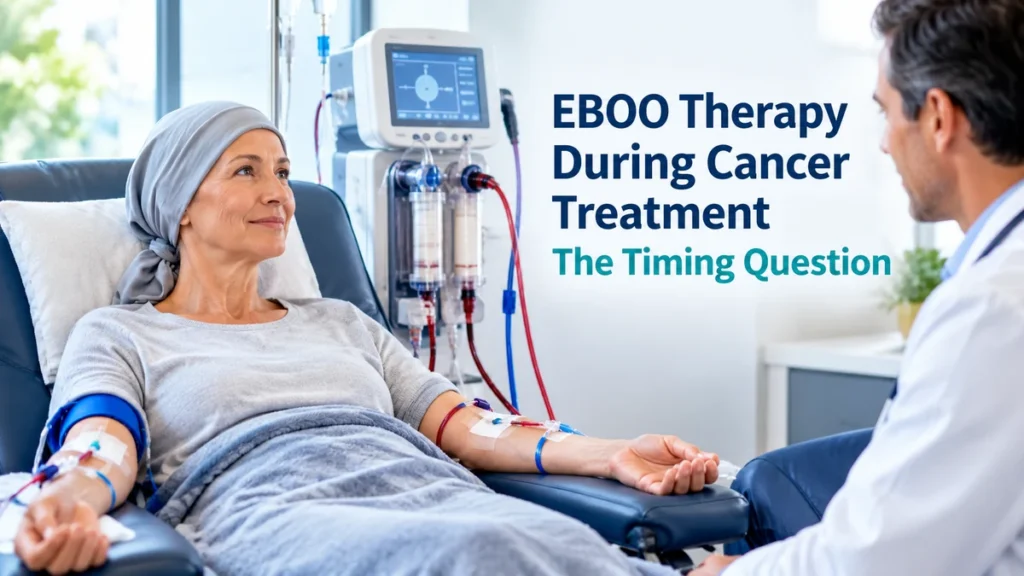
By Dr. Chris Cormier, DC People ask me about EBOO during cancer treatment more often than about almost anything else, and the question they ask is usually the wrong one. They ask whether it works. The question that actually matters first is whether it is appropriate for you, right now, at this point in your treatment — and that answer does not belong to me. It belongs to the oncologist holding your blood counts. So this page is about timing and suitability rather than about efficacy claims. It will not tell you EBOO does anything to cancer, because it does not. Nothing Here Treats Cancer Let me close this off before anything else, because the alternative health field has a genuine problem with this disease. EBOO does not cure, prevent or treat cancer. Neither does ozone, oxygen, light or frequency. No filtration process removes a tumour or alters a prognosis. If you have read otherwise somewhere, that was a claim nobody can support, and acting on it costs people the window in which treatment would have worked. And on colorectal cancer specifically: the thing that reduces your risk of dying from it is screening, which is now recommended from age 45. The CDC screening page sets out the current options, including at-home stool tests. If you are unscreened, that matters infinitely more than anything on this page. What the Procedure Physically Involves EBOO stands for extracorporeal blood oxygenation and ozonation — extracorporeal meaning the process happens outside the body. Blood leaves through a line in one arm, travels through a closed circuit containing a filtration membrane and an oxygenation stage where a medical oxygen and ozone mixture is introduced, then returns through the other arm. It is a continuous loop rather than a withdrawal and a later return, and it runs for roughly 45 to 90 minutes while you sit awake and comfortable. Our full explainer on what EBOO is covers the process in more detail. Two practical points matter more for cancer patients than for anyone else. The procedure requires reliable venous access in both arms, and it places a demand on your circulating blood volume for the duration. Both of those are directly affected by where you are in treatment — which is the whole reason timing dominates this conversation. Why Your Oncologist Decides, Not Us During active treatment, several things change week to week that bear on whether this is safe to do at all. Blood counts. Chemotherapy suppresses white cells, red cells and platelets on a cycle. A low platelet count changes bleeding risk. Anaemia changes what your circulation can tolerate. Neutropenia changes infection risk around any procedure involving vascular access. None of these are visible to me — they are visible in the bloods your oncology team is already taking. Venous access. Many people in treatment have a port or a PICC line, and veins that have taken repeated cannulation. That changes the practical picture considerably. Treatment schedule. Where you sit in a cycle matters. The days immediately following an infusion are not the same as the days before the next one. Medication interactions. Anticoagulants are common in this population and are directly relevant. This is why our answer to someone in active treatment is frequently “not yet”, and why we ask for recent bloodwork and a conversation with your oncologist before anything is booked. A clinic that will book you without either is not being careful with you. What People Actually Come For Afterwards Most of the people we see in this group are past active treatment, and they are not looking for anything to be done about the cancer. They are dealing with what the treatment left behind. Fatigue that does not lift — the kind we write about in our article on EBOO and autoimmune fatigue, which covers much the same ground. Months of lost conditioning. Disrupted sleep. And very commonly, nerve damage — numbness and tingling in the hands and feet, loss of fine motor control, unsteadiness. The regimens used in colorectal cancer are among those most associated with it, and oncology guidance is candid that the drug options are limited. We take the same position here as in our article on oxygen therapy and nerve recovery: this is a nerve problem, and nerve-specific assessment addresses it better than blood filtration does. The Nerve Health Institute article on chemotherapy-induced peripheral neuropathy covers that work in detail. Where EBOO fits for this group is as part of a broader supportive plan, not as the centrepiece. The wider picture is set out in the colorectal cancer support article. Where the Evidence Stands There is a body of published work on ozone therapy generally, much of it European and much of it small. What does not exist is high-quality trial evidence establishing EBOO as beneficial for people during or after cancer treatment. Applying general ozone research to this population is extrapolation, and I would rather name it as such. We set out the same position in more depth in our article on EBOO therapy and detox. Ozone therapy is also not FDA-approved for the treatment of any medical condition in the United States. What people report after sessions is improved energy and clarity. That is worth something, it is consistent, and it is also precisely the kind of outcome that individual reports establish least well. Both things are true, and you should weigh them yourself rather than be handed only the half that sells. What Comes First, and It Is Not This If you are rebuilding after treatment, the things with the best evidence behind them are unglamorous and mostly free. Graded movement within your current capacity, agreed with your team. Protected sleep. Steady hydration. Daylight in the morning. Honest pacing — tracking what each activity costs you the following day rather than the day itself. BodyChargers by Dr. Chris covers that daily side, and it is where most of the ground is actually gained. Get those in place first. If you are
